Repair of Upper Eyelid and Lateral Cathal Defect
Transcript
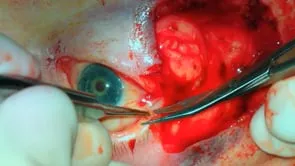
This is Richard Allen at the University of lowa. This video demonstrates repair of a lateral canthal slash upper eyelid defect with a combination of a lateral rotational flap and full thickness skin graft. A rotational flap is planned. This will cover the lateral portion of the defect, which does not cover the eyelid. This is performed so that the eyelid skin can be replaced with a thinner skin graft. Dissection is carried out in the plane of the subcutaneous fat wide undermining is then performed. The flap is then sutured into position with deep interrupted four death Seroquel sutures. A template of the resulting defect is then made. A lateral canaloplasty will be performed with five death sero pro suture. This is placed through the lateral canthal angle followed by the periosteum of the superior lateral orbital rim.
This will result in support of the lateral canthal angle inferiorly. The defect will be attempted to be made smaller by elevating the lateral midface with the four dash sacral suture, which engages the periosteum of the lateral orbital rim. The template is then again placed into position and is trimmed. The flap is then closed with deep interrupted four death zero vicral sutures,
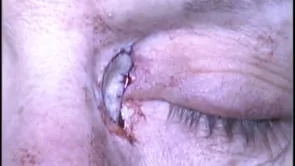
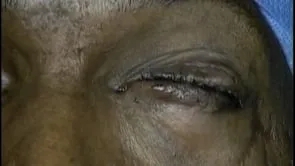
followed by interrupted five death zero prolene sutures. The graft is then harvested from the retro area. Unfortunately, there is a small button hole in the graft. The graft is sutured into position with interrupted five dash sero fast absorbing sutures. Six dash zero silk sutures are placed for bolster fixation. Erythromycin ointment is placed over the graft. A bolster of telfa and foam is placed and fixated into position with the six dash sero silk sutures. The patient will return in one week for bolster removal and reevaluation.